
Surgeons are hot, nurses are cold: the OR thermal comfort gap
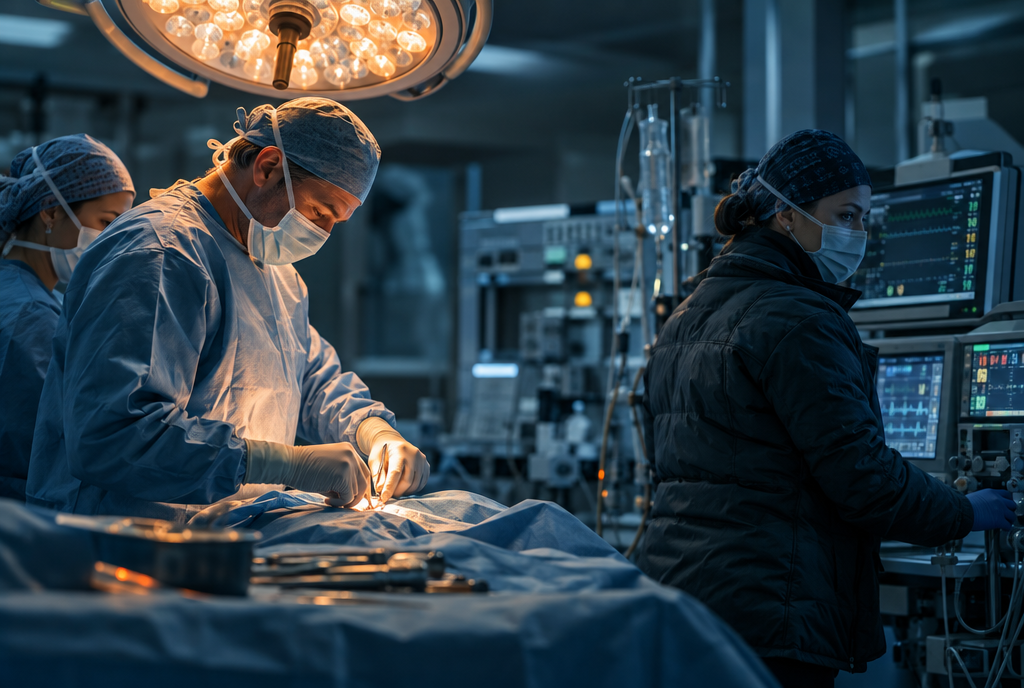
In the same operating room, gowned surgeons working under lights often feel too warm while less active staff, especially anesthesia clinicians, feel cold. Studies using the ISO 7730 comfort method conclude that no single room temperature can satisfy every role. The most effective fixes are role-specific: cooling for scrubbed surgeons and added insulation or warmth for everyone else, within attire policy.
Why do surgeons and nurses feel such different temperatures?
Thermal comfort depends on air temperature, radiant temperature, air speed, humidity, metabolic rate and clothing insulation. In an operating room, the first four are shared, but the last two differ sharply by role.
A scrubbed surgeon stands, works with the arms, wears a sterile gown and gloves, sometimes a lead apron, and may sit under hot surgical lights. An anesthesia clinician often sits near the patient's head, close to the supply airflow, in scrubs alone. A circulating nurse moves around the room but also spends time charting. The same air can feel warm to one and cold to another.
Air movement matters more than many teams realize. Operating rooms use high air-change ventilation, and staff positioned directly in the supply stream lose heat faster by convection than colleagues a few steps away. Radiant heat also varies: the surgeon near the lights gains heat, while a nurse beside a cool wall or equipment cart does not.
What does the research show?
A 2026 study in Atmosphere measured air temperature and velocity in a German operating room with unidirectional airflow, recording 20.1°C to 20.7°C and air speeds near 0.28 meters per second. Applying ISO 7730 at 20.5°C, the authors predicted that 75% of male surgeons wearing 7.5 kg lead aprons would be dissatisfied from heat, while 22% of female anesthesiologists would be dissatisfied from cold. They concluded that a uniform thermal environment cannot satisfy all groups.
Field surveys point the same way. A 2025 study in Energy and Buildings surveyed 254 operating room staff in 19 Nanjing hospitals. Surgeons tended to feel too warm, anesthesiologists tended to feel cold, and circulating nurses reported the highest comfort in that sample. Only 18.2% said the thermal environment had no effect on the operation process.
An earlier Belgian study in Building and Environment compared HVAC standards with ISO 7730 in five operating theaters. It found that technical standards could not produce acceptable conditions for all team members and noted that nurses' cold sensations could be eased with longer-sleeved clothing.
So is it really surgeons hot, nurses cold?
Mostly, with an important correction. The coldest role in these studies is often anesthesia, not nursing. Circulating nurses may be comfortable while moving and cold while charting, and scrubbed technologists can be as warm as surgeons. The pattern is better described as scrubbed and active staff warm, unscrubbed and sedentary staff cold.
| Role | Activity and clothing | Common sensation |
|---|---|---|
| Surgeon | Active, gown, gloves, sometimes lead apron, under lights | Warm to hot |
| Scrubbed technologist | Active, gown and gloves | Comfortable to warm |
| Anesthesia clinician | Often seated, scrubs only, near supply airflow | Cool to cold |
| Circulating nurse | Mixed movement and charting, scrubs | Variable |
Why can't the thermostat just be raised?
Operating room temperature is constrained. ASHRAE Standard 170-2008 sets a design range of 68°F to 75°F with humidity limits, and facilities also weigh surgeon heat stress, patient needs and humidity control. Raising the setting helps cold staff but can push gowned surgeons into heat stress, which a 2023 randomized trial linked to discomfort, sweating and fatigue.
Patients add another consideration. Anesthetized patients lose heat readily, and room temperature is one factor in patient warming plans. Decisions about room settings therefore involve the whole team and the patient's needs, not only staff comfort.
There is also a practical lag. Changing the setpoint mid-case takes time to affect the room, and by then the case may have changed phase. That is one reason many teams prefer to solve comfort at the level of clothing, where each person can adjust immediately without affecting anyone else.
What role-specific fixes work?
The 2026 study recommended active cooling for surgeons and enhanced insulation for anesthesiologists alongside environmental controls. That principle translates into practical steps.
Scrubbed surgeons: cooling vests under the gown, which a 2023 trial found reduced discomfort by 2.1 points on a 10-point scale.
Anesthesia clinicians: warm-up jacket, core vest and warm under layers, plus attention to position relative to supply airflow.
Circulating nurses: layers that go on and off easily as activity changes.
Teams: agree on a starting setting per case type and revisit it at breaks rather than mid-procedure.
How can teams reduce friction?
Temperature disagreements are easier when they are discussed as a known design limit rather than a personal preference. Some teams include room temperature in the preoperative briefing. Managers can support cold staff by approving specific warm layers, and support surgeons by making cooling options available.
Anyone whose cold or heat symptoms go beyond ordinary discomfort, such as dizziness, color changes in the fingers or persistent numbness, should talk to a clinician about those symptoms.
Key takeaways
Metabolic rate and clothing differ by role, so one OR temperature cannot suit everyone.
Studies consistently find surgeons warm and anesthesia clinicians cold; nurses vary.
Room settings are limited by standards, surgeon heat stress and patient needs.
Role-specific clothing, cooling for surgeons and warmth for others, closes the gap better than the thermostat.
Frequently asked questions
Why do surgeons want the operating room cold?
Surgeons wear sterile gowns and gloves, sometimes lead aprons, and work under surgical lights, which traps heat. A cooler room helps them avoid sweating and heat discomfort during long cases.
Who is coldest in the operating room?
Studies most often identify anesthesia clinicians as the coldest group, because they are less active, wear scrubs only and often sit near supply airflow. Circulating nurses vary with activity.
Can surgeons and nurses both be comfortable in the same OR?
Research suggests a single temperature cannot satisfy every role. Combining a moderate room setting with cooling for scrubbed staff and warm layers for others comes closest.
Who controls the OR thermostat?
Most operating rooms have individual temperature controls, and practices differ by facility. Settings are usually agreed within the team, within the facility's allowed range and with patient needs in mind.
Does the OR temperature affect patients?
Yes. Anesthetized patients lose heat readily, so room temperature is one factor in perioperative warming plans alongside active warming devices.
Related reading
Sources
One Operating Room, Two Thermal Worlds: Determinants and Limits of Thermal Comfort for Surgical Staff, Atmosphere (MDPI), 2026
Field questionnaire survey on thermal comfort of medical personnel in operating rooms for hospitals in Nanjing, Energy and Buildings, 2025
Thermal comfort of the surgical staff in the operating room, Building and Environment, 2014
Environmental Conditions for Operating Rooms (ASHRAE Standard 170-2008 summary), Barton Associates
Cooling vest improves surgeons' thermal comfort without affecting cognitive performance: a randomised cross-over trial, Occupational and Environmental Medicine, 2023 (PMC)
About HEATJAC. HEATJAC is a thermal architecture company founded by an anesthesiologist. We design patented garment systems that capture, conduct and broaden warmth across the body, and we publish this knowledge hub because the science of staying warm should be public. HEATJAC products are not medical devices and are not intended to diagnose, treat, cure or prevent any disease.