
Knowledge
Sourced guides on how the body stays warm, how patients and clinicians are kept comfortable, how crews work safely in cold and heat, and how warming gear works. Pick the theme closest to your world.
Ready to choose gear? Browse all buyer’s guides →
Free tools: wind chill and frostbite calculator, cold work warm-up schedule, what to wear by temperature, which warmth setup is right for you? and the warmth runtime and cost calculator. All tools and data →

Science of Warmth
For anyone who wants to understand how the body makes, keeps and loses heat.
Start here
Popular
All Science of Warmth articles →
Healthcare
For clinicians, perioperative teams, hospital leaders, and patients before and after surgery.
Start here
- Patient warming and perioperative hypothermia
- Thermal comfort for clinicians
- For patients: surgery and recovery
Popular
- How to stay warm in the operating room
- What is perioperative hypothermia?
- Forced-air vs conductive warming

Work and Duty
For employers, safety leads, crews, service members and EMS.
Start here
Popular
All Work and Duty articles →
Everyday Life and Health
For people who feel the cold, and for daily life outdoors.
Start here
- Cold sensitivity and Raynaud’s
- Staying warm in everyday life
- Staying warm at home and with family
- Staying warm with a health condition or disability
- Medications and feeling cold
Popular
All Everyday Life and Health articles →
Heat and Cooling
For hot jobs, heavy protective gear and personal heat sensitivity.
Start here
Popular
All Heat and Cooling articles →
Technology and Gear
For choosing, using and caring for warming gear.
Start here
Popular
All Technology and Gear articles →All articles

Heated scrub jackets and warm OR layers: a buyer's guide
Before buying a heated scrub jacket, check five things: whether your facility's attire policy allows a personal or battery-powered layer in your area, where the battery and cord sit, whether the garment can be laundered the way policy requires, whether it fits under a gown or lead apron, and whether a passive heat-reflective or insulated layer would do the job with fewer approvals.

Shivering after a C-section or childbirth
Shivering after a C-section or childbirth is very common and usually harmless. Research reviews report that up to 85% of people shiver after spinal anesthesia for a cesarean, and many shake after a vaginal birth too. It usually settles within an hour or two with blankets and warming. Shaking with a fever of 100.4 °F (38 °C) or heavy bleeding needs prompt attention.
Feeling cold during and after a blood transfusion
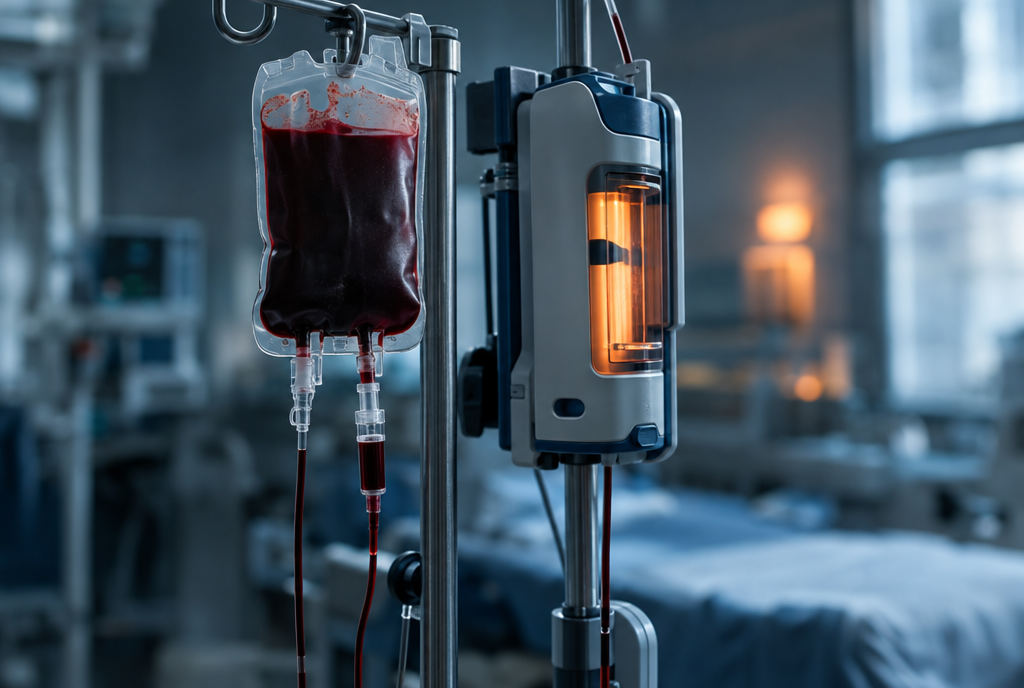
Feeling cold during a blood transfusion can come from the blood itself, since red cells are refrigerated at about 43 °F (6 °C), or from a reaction. Chills with a fever are one of the most common reactions, occurring in about 1% of transfusions. Because chills can also signal a rarer, serious reaction, tell your nurse the moment you feel chilled or shaky.

Why hospital rooms feel cold: patient rooms, the ER and imaging
Hospitals feel cold mostly because of the person, not the thermostat. CDC infection-control guidance lists a design range of 70 to 75 °F (21 to 24 °C) for patient rooms, an ordinary indoor range. Patients feel colder because they lie still in a thin gown, may be ill or fasting, and may receive room-temperature IV fluids. Imaging and equipment rooms can run cooler.

Staying warm while recovering at home after surgery
Feeling cold for weeks after surgery is common and usually reflects recovery itself: blood loss and anemia, eating less, moving less, poor sleep and some medicines all reduce the heat your body makes. In an Australian and New Zealand study of major abdominal surgery, 59% of patients checked before discharge were anemic. Cold with fever, wound changes or breathlessness needs a clinician.

What to bring to the hospital to stay warm: a patient packing list
To stay warm in the hospital, pack layers you control: a robe, a front-opening sweater or zip top that clears IV lines and monitors, warm socks, slippers with non-slip soles and a firm fit, and a soft hat. Leave heating pads and electric blankets at home; many hospitals do not allow them, and nurses can bring warmed blankets instead.

Chills after surgery without a fever: what is normal and when to call
Chills after surgery without a fever are common, especially in the first day or two, when anesthesia, inflammation, pain, a cool room and blood loss can all make you shiver. Chills can also come just before a fever rises, so recheck your temperature. Call your surgeon for a reading above 100.4 °F (38 °C), shaking chills, or chills that start several days after surgery.
Why IV fluids make you feel cold
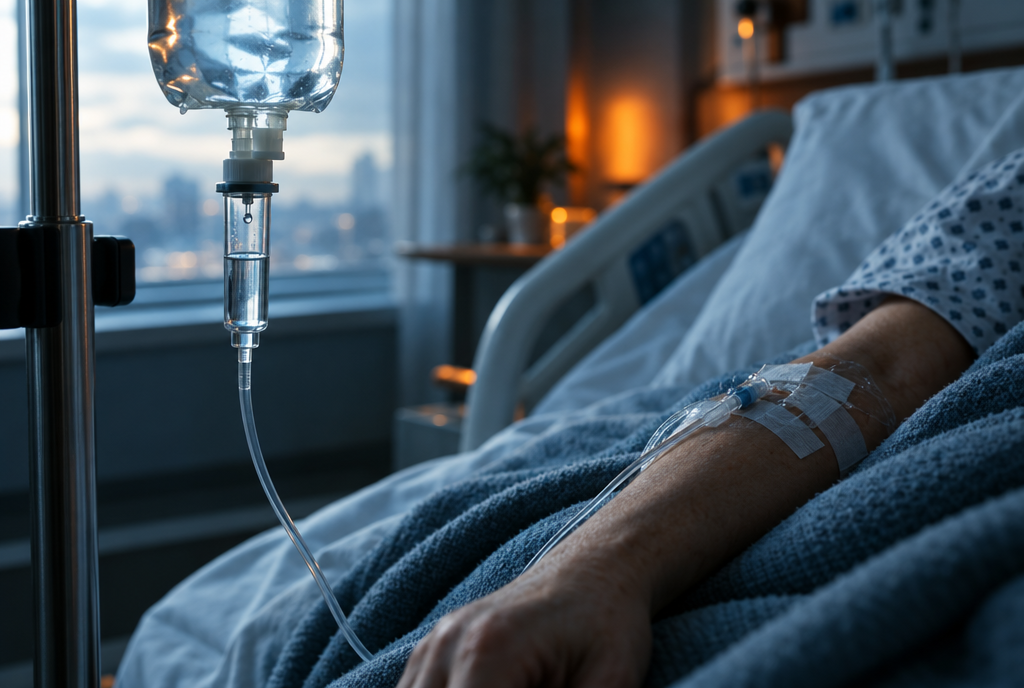
IV fluids make you feel cold because they are usually given at room temperature, well below your body's average of 98.6 °F (37 °C), so your body has to warm every milliliter. Anesthesia teaching material estimates that each liter of room-temperature fluid lowers average body temperature by about 0.45 °F (0.25 °C). The arm with the IV usually feels coldest first.
Perioperative hypothermia statistics: how common it is and what the trials show
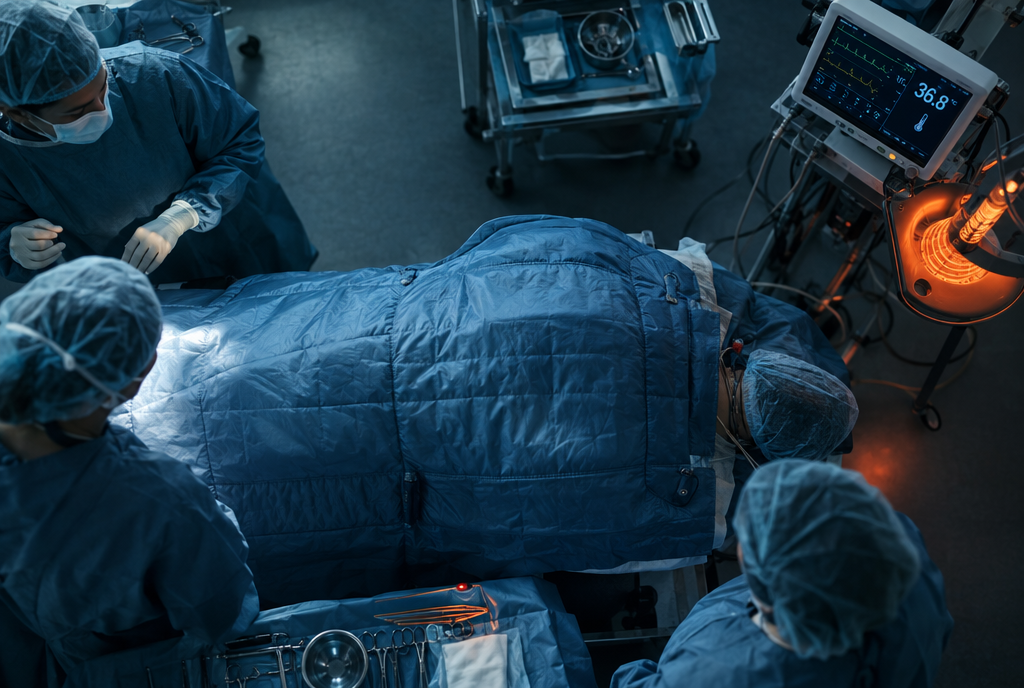
Perioperative hypothermia, a core temperature below 36.0°C under NICE CG65, is common. In a 2015 Anesthesiology study of nearly 59,000 patients warmed with forced air, 64% fell below 36°C in the first hour. A 2017 national study across 28 Chinese hospitals found 44.3%. Rates vary widely with definition, setting and how actively patients are warmed.

Why you feel cold after surgery, and shivering after anesthesia
Feeling cold after surgery is common. Anesthesia blunts the body's temperature control, heat shifts from the core to the skin within the first hour, and operating rooms are cool, so unwarmed patients typically lose 1 to 2°C of core temperature. Shivering after anesthesia is uncomfortable but usually not dangerous, and it normally settles within 20 to 30 minutes with warming.

Gifts for nurses who work cold shifts
The best warm gifts for nurses split into two groups: items they can actually wear at work within their facility's attire policy, such as a low-lint base layer, warm socks in approved colors or a thin core layer under scrubs, and items for off shift, such as a warm commute layer or bedding for daytime sleep. Avoid bulky, hard-to-launder or battery-powered items unless their unit allows them.

Sterile processing temperature rules and how SPD teams stay comfortable
Sterile processing departments set temperature by area. Under ASHRAE Standard 170 (2013 edition as amended by Addendum h), decontamination rooms are designed for 60°F to 73°F, clean workrooms for 68°F to 73°F with humidity at or below 60%, and sterile storage for a maximum of 75°F and 60% humidity. Decontamination runs cool largely because technicians work in heavy, fluid-resistant PPE that traps body heat.

Why dental offices feel cold, and how patients and dental teams stay comfortable
Dental offices often feel cold because the room is set for a team that is moving, standing under bright lights and wearing gowns, masks, gloves and eye protection, while the patient lies still in a reclined chair. Stillness and nervousness both cool the hands and feet. Patients can bring a layer or ask for a blanket; practices can offer blankets and set zones sensibly.

Why dialysis and infusion patients feel cold, and how clinics keep them comfortable
Feeling cold during dialysis is common and usually has several overlapping causes: some of your blood is circulating outside your body, the dialysate may be set slightly cool to help keep blood pressure stable, anemia reduces heat production, your access arm stays uncovered, and you sit still for hours. Infusion patients face similar factors. Layers, blankets and a word with your care team usually help.

How to get a thermal vest approved for use in the OR or clinical areas
To get a thermal vest approved for the OR or other clinical areas, start with your facility's written attire policy. Then take a short, documented request to the people who own each question: infection prevention for fabric and laundering, perioperative leadership for where it may be worn, value analysis for unit purchases, and biomedical or safety staff for anything with a battery.

Warm layers for dentists, hygienists and assistants: a buying guide
Dental team members should buy warmth that lives under the protective gown or lab coat: a thin base layer or close-fitting vest, with sleeves that stay clear of glove cuffs. Warm hands between patients, then perform hand hygiene before gloving. Choose layers the practice can launder under its policy, and for a team, approve a short list of options rather than one item for everyone.
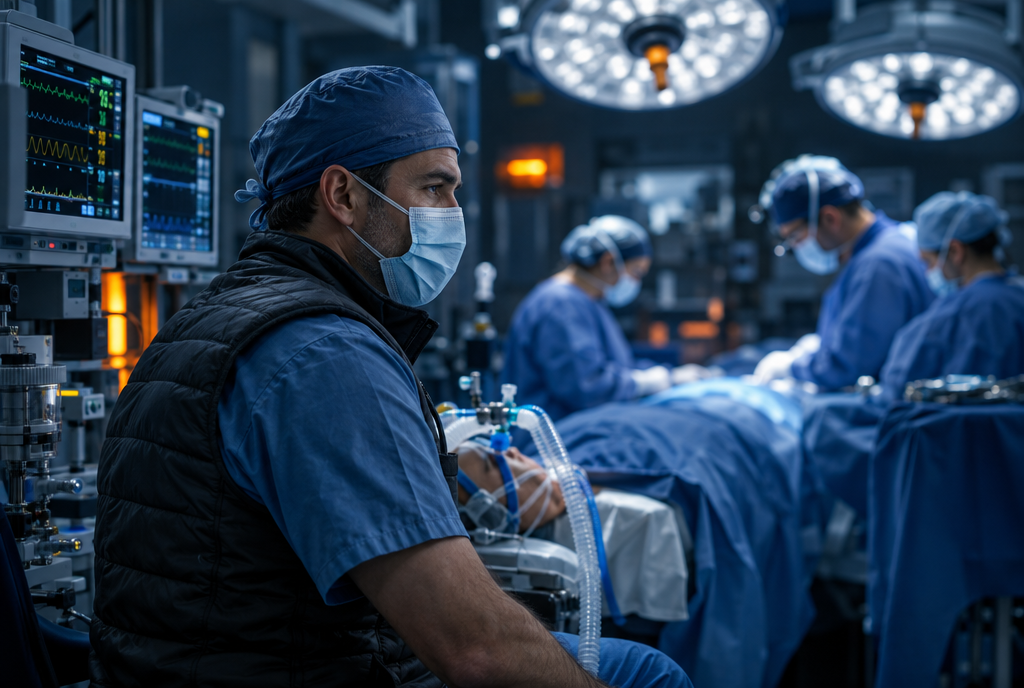
Thermal gear for anesthesia providers: what works at the head of the bed
Anesthesia providers are often the coldest people in the operating room: seated, in scrubs alone, near the supply airflow, for hours. Buy for that position. Prioritize core warmth, sleeves that stay clear of lines and monitors, low bulk at the chest and shoulders, quiet fabrics and closures, and heat you can adjust without leaving the patient. Passive layers avoid most battery policy questions.

What nurses and OR staff should look for in thermal gear
To stay warm under scrubs, buy for your unit's rules first and warmth second: a close-fitting, low-lint base layer, a thin core vest that sits fully under the scrub top, and a warm-up jacket where arms may be covered. Choose fabrics you can launder the way your facility requires. Passive layers suit most units; battery-heated gear fits where devices are clearly allowed.

Core temperature monitoring: methods and accuracy
Core temperature is best measured where blood from the body's core is sampled directly or closely: the pulmonary artery, distal esophagus, nasopharynx or tympanic membrane. Bladder, oral, axillary and zero-heat-flux forehead sensors are practical near-core options with known limits. Infrared temporal and ear scanners are not accurate enough to guide perioperative care, and NICE advises against indirect estimates.

Operating room temperature and humidity standards (ASHRAE 170 and AORN)
In the US, operating room design conditions come from ANSI/ASHRAE/ASHE Standard 170, which sets a temperature range of 68°F to 75°F (20°C to 24°C) and relative humidity of 20 to 60 percent. CMS lowered its minimum humidity from 35 to 20 percent in 2013. The UK's NICE guideline adds a patient-focused rule: at least 21°C (69.8°F) while the patient is exposed.