
Knowledge
Sourced guides on how the body stays warm, how patients and clinicians are kept comfortable, how crews work safely in cold and heat, and how warming gear works. Pick the theme closest to your world.
Ready to choose gear? Browse all buyer’s guides →
Free tools: wind chill and frostbite calculator, cold work warm-up schedule, what to wear by temperature, which warmth setup is right for you? and the warmth runtime and cost calculator. All tools and data →

Science of Warmth
For anyone who wants to understand how the body makes, keeps and loses heat.
Start here
Popular
All Science of Warmth articles →
Healthcare
For clinicians, perioperative teams, hospital leaders, and patients before and after surgery.
Start here
- Patient warming and perioperative hypothermia
- Thermal comfort for clinicians
- For patients: surgery and recovery
Popular
- How to stay warm in the operating room
- What is perioperative hypothermia?
- Forced-air vs conductive warming

Work and Duty
For employers, safety leads, crews, service members and EMS.
Start here
Popular
All Work and Duty articles →
Everyday Life and Health
For people who feel the cold, and for daily life outdoors.
Start here
- Cold sensitivity and Raynaud’s
- Staying warm in everyday life
- Staying warm at home and with family
- Staying warm with a health condition or disability
- Medications and feeling cold
Popular
All Everyday Life and Health articles →
Heat and Cooling
For hot jobs, heavy protective gear and personal heat sensitivity.
Start here
Popular
All Heat and Cooling articles →
Technology and Gear
For choosing, using and caring for warming gear.
Start here
Popular
All Technology and Gear articles →All articles

Passive vs active warming: when each is used
Passive warming reduces heat loss by insulating the patient with blankets, heat-reflective layers or clothing, but relies on the body's own heat. Active warming adds external heat through devices such as forced-air, resistive or circulating-water systems. In surgery, anesthesia blunts the body's heat production and defenses, so guidelines favor active warming for most anesthetized patients and use passive measures as support.

Forced-air vs conductive warming: what the evidence shows
Both forced-air and conductive warming reduce perioperative hypothermia, and neither eliminates it. Forced air has the larger evidence base and is NICE's default; some trials find it slightly more effective, while others find conductive warming equivalent or better, especially when combined with prewarming. Timing, coverage and consistent use often matter more than the choice of technology.
Conductive and resistive patient warming explained
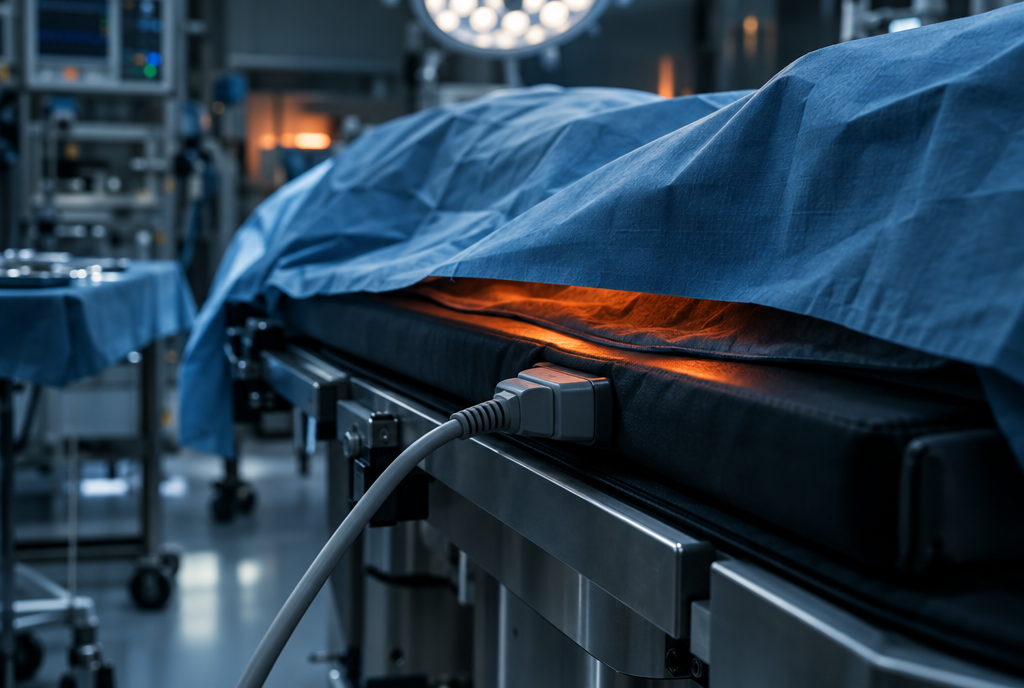
Conductive patient warming transfers heat through direct contact between a warm surface and the patient's skin. The two main forms are electric resistive systems, which pass a low-voltage current through a carbon or polymer fabric in blankets and mattresses, and circulating-water systems, which pump temperature-controlled water through pads or mattresses. NICE recommends considering resistive warming when forced air is unsuitable.

Forced-air warming explained: how convective patient warming works
Forced-air warming blows heated, filtered air from a bedside unit through a hose into a disposable blanket or gown, which releases it through small perforations over the patient's skin. It warms by convection and also blocks radiant loss to the room. It is the most widely used active warming method in surgery and the default recommended by NICE for anesthesia longer than 30 minutes.

Prewarming before surgery: why 30 minutes matters
Prewarming means actively warming a patient's skin, usually with a forced-air or conductive device, before anesthesia starts. It loads heat into the arms and legs so that less core heat is lost when anesthesia dilates blood vessels. NICE recommends starting active warming at least 30 minutes before induction when the patient's temperature is 36.0°C or above.

Inadvertent perioperative hypothermia: NICE, AORN and ASA guidance compared
The three most cited sources agree on the core idea: keep surgical patients at or above 36.0°C. NICE CG65 gives the most specific protocol, including 30 minutes of prewarming and 30-minute intraoperative checks. AORN's Guideline for Patient Temperature Management sets US nursing practice and favors active warming. The ASA standard requires temperature monitoring whenever clinically significant changes are expected.

Cooling vests for surgeons: heat stress under gowns and lead aprons
Cooling vests worn under surgical gowns can make surgeons noticeably more comfortable. In a 2023 randomized crossover trial of 30 orthopedic surgeons, an ice-pack vest cut thermal discomfort by 2.1 points on a 10-point scale and reduced perceived sweating and fatigue, without changing core temperature or cognitive test scores. Vests using ice or phase-change packs suit sterile attire best.

Cold work areas in hospitals: cath labs, pharmacies, labs and morgues
Many hospital areas outside the operating room run cold by design: interventional suites protect equipment and gowned staff, pharmacy cleanrooms control contamination, laboratories and storage areas protect specimens and medicines, and decedent care rooms are refrigerated. Staff in these areas stay warm by layering within each area's garbing rules, adding core warmth, limiting time in the coldest spaces and taking warm breaks.
Surgeons are hot, nurses are cold: the OR thermal comfort gap
In the same operating room, gowned surgeons working under lights often feel too warm while less active staff, especially anesthesia clinicians, feel cold. Studies using the ISO 7730 comfort method conclude that no single room temperature can satisfy every role. The most effective fixes are role-specific: cooling for scrubbed surgeons and added insulation or warmth for everyone else, within attire policy.
Cold hands and dexterity: what the research shows for clinicians
Cold reduces manual dexterity. A classic review set a finger skin temperature of about 15°C as a minimum for hand function, and newer work shows measurable losses can begin at warmer skin temperatures. Warming the hands, and the whole body, helps preserve performance. Operating rooms are not cold enough to reach those extremes for most staff, but cool, exposed hands can still feel clumsy.

Battery-powered personal devices in clinical areas: safety considerations
Personal battery devices such as phones, earbuds and heated vests are common in hospitals, but clinical areas add risks that homes do not. Operating rooms can have oxygen-enriched zones where any ignition source matters, and lithium-ion packs can overheat if damaged or charged improperly. Use certified products and approved chargers, clean devices before entering the OR, and follow your facility's electrical and fire safety policies.

Warm layers and OR attire: infection-control rules explained
AORN's surgical attire guideline allows a long-sleeve scrub jacket, or warm-up jacket, as part of surgical attire and says arms may be covered during patient skin antisepsis. It makes no recommendation on personal clothing under scrubs, leaving fabric and laundering rules to each facility. Scrub attire should be low linting and laundered at a health care-accredited laundry, per state rules, or per CDC recommendations.
Why are operating rooms so cold?
US operating rooms are designed to ASHRAE/ASHE Standard 170, which sets a temperature of 68 to 75 °F (20 to 24 °C) and relative humidity of 20 to 60 percent. Many rooms run at the cool end mainly because surgeons wear gowns under hot lights, and humidity has to be managed alongside temperature. Cold air is not what keeps the room sterile.

Scrub jacket, warm-up jacket or thermal vest: which keeps clinicians warmest?
In surgical settings, scrub jacket and warm-up jacket usually mean the same garment: a long-sleeve jacket worn over scrubs. It warms the arms and is widely accepted when clean and laundered per policy. A thermal vest warms the core with arms free. The warmest policy-friendly combination for most cold clinicians is a low-lint base layer, a thin core vest and a facility-laundered warm-up jacket.

Wearing a heated or thermal vest under scrubs: what to know
You can often wear a thin heated or thermal vest under scrubs, but whether it is allowed depends on your facility's policy for personal clothing, fabric and electrical devices. Passive insulated or heat-reflective vests and pockets for air-activated warmers raise the fewest questions. Battery-heated vests may need approval, especially in operating rooms, and every option should be clean, low-lint and comfortable against skin.

How to stay warm in the operating room: a practical guide for staff
To stay warm in the operating room, layer from the skin out within your facility's attire policy: a close-fitting, low-lint base layer under scrubs, a clean warm-up jacket when arms may be covered, and added core warmth such as a thin vest. Cover your head and feet, keep moving between tasks, eat and hydrate, and ask about room temperature between cases.

What is perioperative hypothermia? Definition, causes and risks
Perioperative hypothermia is a core body temperature below 36.0°C (96.8°F) in the period around surgery. It is common because anesthesia impairs the body's temperature control and moves heat from the core to the skin, while patients lie exposed in a cool room. Even mild hypothermia is linked to more bleeding, wound infection, cardiac events and patient discomfort.
Cold on shift: a clinician's guide to thermal comfort in hospitals
Operating rooms are designed to run between 68°F and 75°F (20°C to 24°C), and many sit near the cool end to protect gowned surgeons and control humidity. That leaves circulating nurses, anesthesia staff and other less active team members cold. The practical answer is layered, policy-compliant attire: a clean warm-up jacket, a low-lint under layer and added core warmth, all within your facility's attire and device rules.
Perioperative hypothermia and patient warming: the complete guide
Patient warming is the set of practices that keep surgical patients at or above 36.0°C, the threshold for perioperative hypothermia. Anesthesia disables normal temperature control and operating rooms are cool, so most patients lose heat without help. Effective programs combine prewarming, active warming with forced-air or conductive devices, warmed fluids, sensible room settings and accurate core temperature monitoring.